Search This Blog

Sunday, June 14, 2020

The Mask: Unmasking the perils while running


Today began my routine 'wogging' after a hiatus of over 3 months. Things looked the same, crowds the same. People were greeting each other like long lost friends. The grass was overgrown and heads shaved. But there was an extra piece of apparel donned by all, which in most cases covered the mouth and nose, in some only the mouth and the rest, it lay resting around the neck. That was the MASK. They seemed to have different forms and numbers - a surgical 2/3 ply,
Surgical mask
Wildcraft mask
N95 mask


a reusable Wildkraft, a hanky or an N95. People wore them either out of compulsion or just for caution. But I need to caution you about the perils of wearing these MASKS while walking or running and the risks of unmasking certain health conditions by an overzealous training effort. 

While doing moderate to high intensity exercises or running, the breathing rate increases and so does the air requirement. A face mask is going to decrease your airflow, making it a little harder to breathe. It won’t decrease your oxygen or retain carbon dioxide. But it will definitely impact your performance or pace.
In such a situation a tight fit N95 is a strict no-no. A regular mask may also be uncomfortable with such exercises. So a practical solution to this could be wearing the mask around the chin or neck while running and maintaining a strict 6 feet distance with others and when you are about to cross a person, you could just lift up the mask to cover the mouth and nose. 
The masks also tend to become damp due to sweat and our breath. To overcome this, try breathing through your nose. That reduces the vapours and also allows air to get filtered through the nasal passageways. 

Watch for symptoms like lightheadedness, dizziness, numbness or shortness of breath. Abandon the day's workout if you experience any of the above and consult your doctor.

Here is the silver lining - even though the mask may diminish your performance for the first few times you wear it, your body will ultimately adapt. Once the mask is removed after few weeks or months of training, the lungs will have the ability to intake and absorb more oxygen, which would most likely result in a performance increase. 

The risk of transmission of the virus outdoors is much less as compared to a closed room. Hence open air jogging, running or cycling should be preferred to gym activities. 
A low intensity workout is preferable initially to adjust to breathing through a mask.

People suffering from chronic respiratory ailments like asthma, COPD, etc should prefer indoor exercises at home without a mask to ensure safety for themselves and others.

Also, after an almost sedentary period of 3 months, a sudden burst of exercise can unmask underlying health problems and precipitate a heart or asthma attack. 

Don't push your limit: Do not go overboard when exercising. If you start feeling tired, then stop. 


Sunday, July 23, 2017

Does medical science believe in miracles?

July 2012: Mr Abdul Rehman Shaikh,  75 year old male was hospitalised in the ICU with sudden paralysis of the right side of the body. A diabetic since 20 years and ischemic heart disease with a poor cardiac function since 10 years, his regular activities had already reduced  due to a poor heart conditioning. And now to increase his morbidity, he had had a stroke, which affected his left or dominant side of the brain. He lost his speech, the power to move his right hand and leg, control over his bladder and bowel movements, but not his power to live. He was discharged after a few days in a bed ridden state with a poor chance of long term survival. 
But the worst was far from over. Within a few days, he was back at the hospital with a gangrene of the foot. The blood supply to the leg was found to be very poor due to long standing diabetes. As a result of this, his left foot had to be amputated. His heart which was already compromised, couldn't take it further, and he suffered a cardiac arrest in the hospital. Due to the resuscitation efforts of the medical personnel, Mr Shaikh did survive, but suffered extensive irreversible damage to his brain. The doctors did manage to get him off the ventilatory support, but he had slipped into a vegetative state for life. He now had a feeding tube,a breathing tracheostomy tube to aid the removal of his tracheal secretions and a urine catheter. He barely opened his eyes, neither responded to anybody's touch nor call, and was mechanically fed by the nurses. The doctors had given up hope completely this time and sent him home with no chances of survival. 

July 2017: 5 years have passed. Every 6 months, he is brought by his daughters to the hospital for a routine physical checkup, a change of tubes, and a battery of investigations. 
The results always amaze the doctors. They find no deterioration in any parameters. The sugars are well controlled, the lungs are breathing normally, the heart is pumping with the same force as before, there is not a trace of a bed sore and not an iota of infection in the urine. Neurologically he may be the same, but we are still hoping for Abdul Rehman Shaikh to get up and talk to us. 

This is not a miracle but a dedicated effort by the near and dear ones to keep the hope alive. On one hand we have sons who ask us on just the second day of ventilatory support, "Doc, should we remove the respirator and take our papa home" and on the other hand we have a certain Mr Shaikh's daughters who despite the doctors giving a 'no chance' certification, have persevered with their efforts. 

*Names have been changed to protect the identity

Tuesday, June 27, 2017

Dialysis: A life saving machine

A 70 year old diabetic lady, hitherto active and leading a normal lifestyle, is admitted in the Intensive care with sudden difficulty in breathing since 2 days. After running a few tests, she is diagnosed with Acute kidney failure because of an infection in her urine. She has been advised an urgent lifesaving dialysis but her relatives outright refuse to go ahead with it. Their concern is that once started, she would require dialysis on a regular and lifelong basis. 
To convince someone for dialysis remains one of the commonest challenges faced by Internists and Nephrologists. In a country where quacks sometimes decide the course of medical therapy, where pharmacists prescribe scheduled drugs and where relatives are in charge of the fate of patients, saving lives is becoming more and more difficult. 
What is dialysis? Simply put, it is an artificial kidney. Our kidneys normally function to remove the waste products through the urine. When there is a kidney failure, dialysis takes up the function of the natural kidney and cleanses the body with the help of a machine. 
Broadly put, our kidneys may fail in 2 ways: 
1. The healthy kidneys stop working suddenly due to a recent crisis event. 
2. The kidneys are gradually damaged over a long period of time. The body adjusts to this and maintains its milieu till a crisis develops and the kidneys fail.
                       
It is important to note that kidney failure occurs only when both kidneys fail to function. In both the above situations, dialysis may need to be done for the reasons mentioned above. Also, dialysis doesn't help in kidney recovery but it just substitutes for the failed kidneys. But, it needs to be emphasised here that in the first case, since the kidneys were healthy prior to the illness, dialysis is only for a short period of time while in the second case, dialysis could probably be a lifelong affair.                              That brings us to a few important questions. Shouldn't saving a life be the topmost worry on the minds of the near and dear ones rather than worrying about whether the dialysis will be a lifetime headache? Don't the relatives have any responsibility ethically and legally towards the patient? Is only the doctor answerable for a wrong decision taken for a patient? 


And in our 70 yr patient, who eventually died because she was denied a chance to live, can the relatives be tried in court for negligence and malpractice??

Friday, September 18, 2015

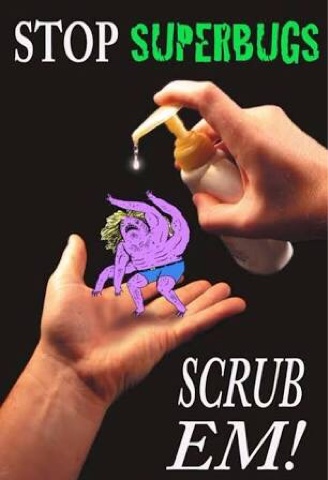
Superbugs: Born to kill

Antibiotic resistance: The ability of bacteria and other microorganisms to resist the effects of an antibiotic to which they were once sensitive. It is also known as 'drug resistance'. 
This makes the medications less effective and as a result of which higher doses of drugs are needed which would result in more side effects. Organisms which are resistant to multiple drugs are called 'Multi drug resistant -MDR' or "Superbugs".  

Antibiotic resistance is a serious and growing global problem: a WHO report released April 2014 stated, "this serious threat is no longer a prediction for the future, it is happening right now in every region of the world and has the potential to affect anyone, of any age, in any country."

India is the world's antibiotic popping capital, recording the highest number of such pills consumed annually- 13 billion, as against 10 billion in China and 7 billion in the U.S.  

What are the Indian causes for such an emergence of resistance ? 

1. Self medicating oneself by indiscriminately prescribing some irrational antibiotic. 
This is generally done by patients to save themselves the trouble of visiting a doctor. Very rarely does one succeed in treating in this manner. 
The worse situation arises when the patient self medicates and stops the antibiotic without completing the entire therapy. Perfect recipe for developing drug resistance. 

2. The other group of patients would rely on their local B Pharm chemist to dispense them some antibiotic rather than visiting a doctor. It is termed as OTC- Over the counter. This is one of the reasons why the FDA has come down hard on these retail chemist outlets. 

3. Doctors are equally to blame for this rising incidence of resistance. When the patient visits his or her General Practitioner or Family Physician with say a Viral Fever, he is prescribed an antibiotic for a few days knowing full well that an antibiotic has no role in a Viral illness.  If the fever doesn't subside, an anti malarial is added to the treatment without subjecting the patient to a battery of tests to confirm the diagnosis. Doctors are sometimes also guilty of starting Anti tuberculous treatment without sufficient evidence of the disease. 

4. Once the patient is hospitalized, the Consultant takes over the case. He generally starts with a higher and broad spectrum antibiotic since he doesn't want to take any chances. This attitude over a period of time aggravates the resistance problem and thus we see the emergence of the Superbugs. 


There is an urgent need to formulate guidelines. It is a common practice in the West to start with basic antibiotics like Co-Trimaxozole while in India we would prefer to start straightaway with a 3rd or 4th generation Cephalosporin. 

  • Antibiotics should only be used when needed and only when prescribed. 
  • Health care providers should try to minimize spread of resistant infections by using proper sanitations techniques including handwashing or disinfecting between each patient. 

  • Prescribing the correct antibiotic is important and doses should not be skipped. 
  • The shortest duration needed should be used. 
  • Narrow-spectrum antibiotics should be used rather than broad-spectrum antibiotics when possible. 
  • Cultures should be taken before treatment when indicated and treatment potentially changed based on the susceptibility report.


"It is not the human body that is resistant, it's the organism which gets resistant". 

Friday, January 30, 2015

Flu: Can we fight it?


Influenza, commonly known as flu, is a viral illness characterized by fever, runny nose, cough and muscle pains. Most often it is a self limiting ailment lasting for less than a week.

SHOULD ANTIBIOTICS EVER BE GIVEN FOR INFLUENZA?
Only 16% of patients with Influenza were prescribed Antivirals whereas as many as 30% were prescribed antibiotics. Unfortunately, we know that if you go to a Physician for a flu, you are more likely to leave with a prescription for antibiotics that you don't need than for an antiviral that might do you some good. 


If antivirals are started within 48 hrs of onset of symptoms, there will be an improvement of 30 hrs in time to getting better but if they are started after 48 hrs, there is not much benefit.

The problem might be a consequence of a lack of familiarity with antivirals and confusion over when to use and when not to use them. Also, there is a "deeply ingrained tendency" to prescribe antibiotics for sick patients because they need something or because of the perception that patients are going to be happier.
Inappropriate usage of antibiotics has thus led to a major crisis in antibacterial resistance.


Another very important reason is that clinicians 'don't want to risk missing anything'. Even if they know that out of 99 influenza cases, fewer than one will have a bacterial superinfection, physicians don't want to have not treated that one person who develops bacterial pneumonia as a complication of flu. It is true that flu predisposes to bacterial pneumonia, but it is not true that giving an antibiotic will prevent it, because the patient is likely to be infected with a different bacterium from the one targeted by the antibiotic. And if you treat 100 patients who don't need an antibiotic, you are probably going to send one to the hospital with a rash. If several develop diarrhea you will do far more harm than good.

SHOULD FLU SHOTS BE GIVEN TO ONE AND ALL?

Prevention is better than cure they say. A shot of the Influenza vaccine at the beginning of the cold season is recommended for everybody above the age of 6 months especially those at high risk - Immunocompromised, asthmatics, diabetics, etc. But the prevention rate is a measly 23%. The virus has a very high tendency to mutate and change its form. As a result, the antibody produced against the virus fails to destroy it. Also, the improper maintenance of the cold chain for preserving the vaccine has led to the high failure rate. Despite all this, the vaccine should be administered as advised since the benefits however small they seem, far outweigh the zero risk. The vaccine protects against certain strains of influenza, including the B viruses, which can cause severe disease and complications in infants, young children, and the elderly.

"Someone told me that they didn't want to take a flu shot because they didn't want to put a foreign substance in their body. What do they think they do at dinner every night?"

The flu is very unpredictable when it begins and in how it takes off.

Excerpts from Medscape

Saturday, November 22, 2014

Drug patents: The battle goes on…..


The war between Generics and Brands doesn't seem to die down. In our last discussion, 
we had concluded that the basic difference between these two is the pricing, a marginal difference in the efficacy of both the variants and the safety profile was but obviously assured. Probably that was what we were made to believe.


India Today.in
The latest incident involving 13 female deaths at the Bilaspur sterilization camp has served as an eye opener.
As a knee jerk reaction, the honorable doctor who performed the surgeries at the camp was apprehended and charged with negligence and homicide.

Investigations have now revealed the presence of zinc phosphide, a rodenticide, in Ciprocin 500 (antibiotic), which was prescribed to all the patients during surgery.
This generic drug was manufactured by Mahawar Pharma Pvt Ltd, a Chhattisgarh-based drug firm, a small drug company according to revenue figures disclosed by the company.
This company has a very small unit in Raipur. They have been in the business for over 30 years now but it's a small scale business and supply of medicines was restricted within the state.
Political connections might have helped the company, despite reports that it was blacklisted two years ago over sale of duplicate generic drugs.

This may be a stray incident involving generic drugs but it certainly cannot be passed off without learning a lesson or two.

Firstly, it is important to realize that even the leading pharma companies do manufacture generics. The quality would obviously be ensured with such products.

Secondly, it is always better to avoid medical procedures and treatments in camps. Due to the large numbers, sterility can often be compromised.

And lastly. Dear doctors, if you ever have to participate in a medical camp, please ensure that the medical and paramedic staff are competent enough, drugs are of a standard quality and the setup fulfills the basic needs of a medical centre. Even though you haven't charged for your services, you are still answerable to the consumer forum.

A couple of weeks back I happened to meet a doctor colleague of mine from the US. He had remarked.  " The fundamental difference between the health system in our country and yours is that we value human lives". His words still keep ringing in my ears. 

Monday, November 17, 2014

Cell Phones: Savior or……...

The cell phone has provided an amazing safety net for citizens of almost all cultures across the world. The lives saved by the proliferation of cell phone communication is phenomenal — emergency calls, quick first responders, warnings of severe weather are only a few examples. However, the potential role of cell phones as an additional factor in oncogenesis (cancer creation) can't be dismissed.

The largest-ever study on the topic—the International Interphone study, which was conducted by the International Agency for Research on Cancer (IARC) and funded in part by cell phone companies, published in 2010, failed to find strong evidence that mobile phones increased the risk of brain tumors.

The IARC released a report in 2013, suggesting that there is a possibility of brain tumors amongst users of  both mobile and cordless phones.


But, the latest research on the subject concludes that long-term use of both mobile and cordless phones is associated with an increased risk for glioma, the most common type of brain tumor.

The new study published online October 28 in Pathophysiology, shows that the risk for glioma was tripled among those using a wireless phone for more than 25 years and that the risk was also greater for those who had started using mobile or cordless phones before age of 20 years.

This increased risk is due to greater exposure to radiofrequency electromagnetic fields. The brain is the main target of these emissions when these phones are used, with the highest exposure being on the same side of the brain where the phone is placed.


Children and adolescents are more exposed to radiation than adults because of their thinner skull bone and smaller head and the higher conductivity in their brain tissue. The brain is still developing up to about the age of 20 and until that time it is relatively vulnerable.

Radiation exposure increases dramatically when cell phone signals are weak.


Girls and doctors tend to put the smartphone below the pillow.
"It's a bad habit to go to bed with your smartphone."

It's time we minimized our risks.
Using hands-free phones with the "loud speaker" feature and text messaging instead of phoning should always be encouraged in appropriate settings.

"Technology can be our best friend, and technology can also be the biggest party pooper of our lives. It interrupts our own story, interrupts our ability to have a thought or a daydream, to imagine something wonderful, because we're too busy bridging the walk from the cafeteria back to the office on the cell phone" - Steven Spielberg. 

Friday, October 31, 2014

Malaria: The Growing Menace

The growing incidence of drug resistance has become a cause of worry for the medical practitioners. Very soon we would be left with hardly any choices to combat the infectious agents. 

The common causes for this emerging resistance are:


  • Misdiagnosis
  • Incorrect choice of therapy
  • Inappropriate doses
  • Incomplete therapy

As much as we blame patients for stopping the therapy before its completion,  so also we should be blaming ourselves for incorrectly prescribing the treatment.   

I have laid down the basic guidelines for the outpatient therapy of uncomplicated Vivax and Falciparum malaria.  

As adapted from the "National Vector Borne Disease Program" (NVBDCP)- 2013:


Please make note that Primaquine needs to begin from Day 1 of therapy. 


Drug schedule for treatment of P falciparum malaria:


Thus, the cornerstone of malaria treatment is Artesimin based combination therapy (ACT). 
ACT could either be a combination of Artesunate + Sulfadoxine-Pyrimethamine
Or
Artemether + Lumefantrine.

As discussed above, Primaquine is a very integral part of the therapy in both Falciparum as well as Vivax malaria.

In Falciparum, it is given on Day 2 as a single dose of 45mg, to eradicate the gametocytes and thus prevent the further transmission of the parasite.

In Vivax, it is given from Day 1, 15mg per day for 14 days, to eradicate the hepatocyte stage seen only in vivax malaria.


"Together we can, together we will".

Wednesday, September 24, 2014

A diagnostic challenge: Dengue vs Chikungunya

Couple of days back, a 30 yr old lady came to me in a panicky state for a second opinion, complaining of fever, joint pains and muscle pains since past 3 days.  A routine blood analysis for fever showed a Positive result  for the IgG anti- Dengue antibodies whilst the IgM anti-Dengue antibodies was Negative. The anti-Chikungunya antibodies were negative. So were the rest of the investigations. 
She was diagnosed as Dengue fever and advised hospitalization. 

I begged to differ as regards the diagnosis. At the outset, it seemed like a Viral episode and I prescribed her Paracetamol and advised bed rest. Over the next few days, her platelet counts remained normal and her fever subsided. She followed up after 2 weeks however, still complaining of joint pains and stiffness. A repeat analysis this time showed a positive result for Chikungunya IgM antibodies. 
Thus, the diagnosis changed from first Dengue, then to Viral fever and now finally Chikungunya. 

The question that would be on every body's mind is: 
1. Wouldn't a false diagnosis hamper the treatment and 
2. How would you differentiate clinically between all these three ailments? 

Let me explain. First and foremost, all the three are forms of Viral fever. So, the basic management remains same in all of them. 

Differentiating features:
The dengue and chikungunya viruses are both transmitted by Aedes species of mosquitoes.
The distinguishing feature of chikungunya includes potentially debilitating bilateral joint pains and, in some cases, arthritis. 
And a significant drop in platelet counts is mainly observed in dengue. 

Fallacies of testing:
During the first few days of the illness, the antibodies may remain undetected in blood and hence Dengue may be missed unless the Spot or Antigen test is performed. 
Clinicians should also be aware that detection of anti-Dengue IgG antibody has very little utility in the diagnosis of acute dengue, as IgG antibodies may be the result of an infection that occurred in previous months or years. In addition, IgG antibodies against other viruses can cross-react with Dengue, thereby yielding false-positive diagnostic results. 

Management:
Chikungunya is rarely fatal. In contrast, early identification and proper clinical management for dengue cases can significantly reduce the fatality. Therefore, patients suspected of having dengue or chikungunya should be managed as having dengue until dengue can be ruled out. 
Most patients who develop severe dengue do so in the 24-48 hours after fever subsides and this can occur rapidly. Hemodynamic status should be maintained with judicious use of isotonic intravenous fluids, which is the central component of dengue patient management. 
Pain and fever in patients with suspected dengue or chikungunya should be managed with acetaminophen or Paracetamol. Aspirin and other NSAIDs should not be given to such patients because of the increased risk for bleeding manifestations if the patient has dengue. If patients have been afebrile for at least 48 hours, have no warning signs of severe dengue, and still complain of joint pain, NSAIDs may be considered. 

The list of viral fevers is too exhaustive to elaborate and it is practically impossible to clinically differentiate one from the other. The prototype always would remain the Influenza virus or "flu". But most often than not, these are self limiting and unless there is an added bacterial infection, antibiotics wouldn't work for these viruses. 

Sunday, January 26, 2014

Does Aspirin a day really keep the doc at bay?

The benefits of the common practice of taking an aspirin a day to keep the doctor away, are now under serious dispute. 

Various authors have argued for time immemorial that the benefits of aspirin far outweigh the risks. Not only does aspirin provide protection against cancer, but it also reduces the risk for heart disease and stroke. An aspirin daily can certainly seem like the ultimate supplement and it is very inexpensive.
There were also talks of Aspirin being included in the community water supply so that people would benefit from it. 

This practice is now all set for a change. 
Critics have started panning this molecule. 
Their claim is that there is no evidence that aspirin is effective for the primary prevention of  acute coronary syndromes and stroke. Even if benefit does exist, it may not outweigh the harm. Also, there is no evidence that long-term aspirin should be given to patients even with known cardiovascular disease. 

It is possible that when a stable plaque has ruptured, it becomes unstable, resulting in a coronary 'ulcer'. This is a focus for thrombus generation. Aspirin acts here by inhibiting thrombus propagation. However, once the acute event is over and the 'ulcer' has healed, any reduction in platelet aggregation by aspirin may be offset by inhibition of prostaglandin-mediated vascular wall defences and the increased risk of plaque haemorrhage.

Thus, aspirin, just like an antibiotic, should be given for an acute illness and stopped when the acute syndrome has settled. This could be for a period ranging from 1-6 months. 

Aspirin use is associated with an increased risk of 
  • Dyspepsia, gastro-intestinal bleeding leading to anemia. In patients with cardiovascular disease, iron deficiency anemia is associated with a poor prognosis. 
  • Chronic kidney disease and renal dialysis. 
  • Haemorrhagic stroke. 
  • Possibly deafness and age-related macular degeneration. 
Aspirin may also lessen the benefits of drugs that are known to reduce cardiovascular risk, such as angiotensin-converting enzyme (ACE) inhibitors and possibly beta-blockers. 

On a positive side, aspirin prevents vascular proliferation in tumours preventing their growth, thus retarding the progression of bowel and other cancers. 

There is no denying the blood thinning properties of Aspirin for those with heart problems but there is very little justification to insist that everyone needs to take an aspirin. 


"Advice for the day: If you have a headache, follow the instructions on the bottle. Take 2 and KEEP AWAY FROM CHILDREN. "


Sunday, November 17, 2013

Drug- Drug War: Clarithro vs CCB

The antibiotic clarithromycin prescribed for patients already taking antihypertensive calcium-channel blockers is associated with increases in hospitalization for acute kidney injury, hypotension, and death, according to new research.


Clarithromycin is an inhibitor of the cytochrome P453A4, the enzyme that metabolizes calcium-channel blockers. The antibiotic can send blood concentrations of calcium-channel blockers soaring by as much as 500% leading to severe hypotension. 

Patients on regular treatment with calcium channel blockers like Amlodipine, Felodipine, Nifedipine, Diltiazem or Verapmil were prescribed Clarithromycin or Azithromycin. These macrolide antibiotics are commonly used for upper respiratory infection, pneumonia, eradication of H. Pylori, and atypical mycobacteria. 

Because azithromycin is only a weak inhibitor of CYP34A, the type of intensification of the calcium-channel blocker that occurs with clarithromycin is not expected.

Also, due to the role of the kidneys in eliminating clarithromycin, guidelines call for reduced dosing of the antibiotic in patients with chronic kidney disease. 

Thus, it is highly advisable, in patients suffering from high blood pressure and on regular medications, to be wary of the antibiotics prescribed or used over the counter. 

Published: November 9 in JAMA 

Sunday, September 08, 2013

Asepsis and Dementia: Can there be a possible interaction?

I have always been taught by my parents the virtues of staying clean and maintaining a good hygiene all through out my life. Being a Muslim, we have to offer prayers 5 times a day. But these cannot be offered without the ablutions. So that means we need to cleanse ourselves at least five times in the day. 
Being a doctor, our professors have always harped on the compulsory aseptic precautions, be it the out patient department, regular routine rounds, or the peri operative wash up.  
The benefits of cleanliness are endless. 
Thus, when my hospital staff showed me this news clipping, I was taken aback. 

Shocking but true. 

An obsession with being too clean and hygienic could lead to a higher risk of dementia, researchers have warned.

Researchers say that people living in wealthier countries may be at higher risk of developing Alzheimer's disease, according to a study published in the journal Evolution, Medicine, and Public Health.
The researchers suggested the ‘hygiene hypothesis’ was behind the difference. This is the theory that an excessively clean lifestyle doesn't allow us to develop immunity levels and thus we are unable to combat many germs.

Results of the analysis revealed that countries with higher levels of sanitation and those with significantly lower rates of infectious disease also had higher rates of Alzheimer's disease.   

Shocking but true.

Thus, I would conclude on this note that   the people suffering from OCDs (Obsessive Compulsive disorders), who repeatedly get the urge to wash and clean themselves, are in for a rude shock. They now have to deal with another neurological issue - Dementia. 

Thursday, August 29, 2013

First time lucky, or unlucky

Whoever would have thought that the first child born (primogeniture) would be a riskier one?

The first one is more intelligent with a higher IQ than the later siblings probably due to the fact that he or she is the 'pearl of the eye' and gets lavish attention from parents that boosts the intellectual development. 

But medical literature antagonizes this. 
Recently, evidence has emerged on the consequences of primogeniture on long-term metabolic and cardiovascular health risks.


There has been a steady decline in the birth rates in the world owing to many factors which include family planning measures, government policies (one child norm) or economic constraints. As a result of this, we have a large percentage of one-child families. Since the first child is prone to health issues, we are now staring at a future population with a high proportion of risk factors. 

Despite similar gestational ages, first borns are 250g lighter than the later siblings at birth. Changes in the placentation are accounted for this difference in birth weights. 
Low birth weight is an indirect indicator of poor intrauterine milieu and adverse health outcomes have been demonstrated in association with decreasing birth weight. Offspring of mothers exposed to nutritional or physiological stress during pregnancy are at increased risk of metabolic and cardiovascular disease in later life. There is extensive evidence linking a reduction in birth weight with increased risk of insulin resistance, Type 2 diabetes mellitus, hypertension, cardiovascular disease, stroke and cancer.

First-born children are taller than the second or third child. Taller stature in childhood is positively associated with overweight status and obesity later in life. 

Various statistics suggest that first-borns were more likely to develop Type 1 diabetes mellitus, hypertension, heart disease, allergic disorders and psychological issues. 

Primogeniture are the largest identifiable study group (accounting for more than half of the world's population), so that any associated health risks could have enormous public health consequences.

Monday, July 29, 2013

Obesity: The Pandemic


Obesity is defined as abnormal or excessive fat accumulation that may impair health.

Body mass index (BMI) is a simple index of weight-for-height that is commonly used to classify overweight and obesity in adults. It is defined as a person's weight in kilograms divided by the square of his height in meters (kg/m2).

The WHO definition is:

a BMI greater than or equal to 25 is overweight
a BMI greater than or equal to 30 is obesity.


Obesity is a major public health problem in the world. Two thirds of adults in the  US are overweight, and one third are obese. Being obese increases the risk for other diseases: high blood pressure, heart disease, type 2 diabetes, osteoarthritis, sleep apnea, and even some cancers.


The American Medical Association (AMA) House of Delegates has in June 2013 redefined Obesity from a major public health problem to a Disease. After much debate, the majority ruled that obesity is a disease state with multiple pathophysiologic aspects requiring a range of interventions to advance obesity treatment and prevention. 

This has now given an entirely different perception to this potentially hazardous malady. 

"OBESITY IS A DRIVER OF MUCH SUFFERING, ILL HEALTH, AND EARLIER MORTALITY."

The two sides of the coin : 

  • Here's the downside of calling obesity a disease. Some worry that this would medicalize obesity and intensify reliance on drugs and surgical treatments rather than relying on diet and exercise to attain a healthy weight. Another concern is that calling obesity a disease could alienate some obese individuals, especially if the emphasis is on achieving ideal weight rather than focusing on healthy eating and increasing physical activity. 
The Body mass index (BMI), that obesity is defined on the basis of, has many limitations. It was originally designed as a research tool: a rough population-level indicator. It's not a great way of measuring body fatness. Some people with a BMI in the so called "normal" range can have too much body fat, as well as metabolic problems. Some with BMIs over 30 kg/m2 -- the so-called obese range -- have plenty of muscle and no excess fat . Some with high BMIs are normal metabolically and also have normal blood pressure and cholesterol levels.

The BMI defines size, not health. 

The National Heart, Lung, and Blood Institute is now working on new guidelines on overweight and obesity in adults. 


  • Here's the pro side. Calling obesity a disease could mean greater investments by the government and the private sector: more research into causes, triggers, and treatments, including more US Food and Drug Administration (FDA)-approved drugs for treatment. Another benefit of making obesity a disease is that it could make it harder for third-party payers to deny coverage.


Obesity paradox: 

A collection of studies suggests that BMIs in the overweight or obese range may have protective effects on mortality risk. 
Experts have suggested that body fat may play a protective role, perhaps in secreting certain beneficial cytokines and hormones. Extra body fat also means extra padding and thus a physical protective barrier from traumatic injuries. In times of illnesses, the additional caloric reserve may give patients more nutritional backup in the healing process. 

However, the ill effects of the excess fat are too pronounced to be ignored. 

The most important advanced technology with which to fight obesity is the bathroom scale, used every day. Don't let that number rise. 

Obesity, after being categorized as a disease, we can now expect that the development of gray hair or the aging process- Senility, to be the next condition considered as a disease.